Bilateral carpal tunnel syndrome in a man over sixty is not always idiopathic. In a non-negligible proportion of cases, it is the first manifestation of a systemic disease that will affect the heart years later.
Why amyloidosis begins in the hand
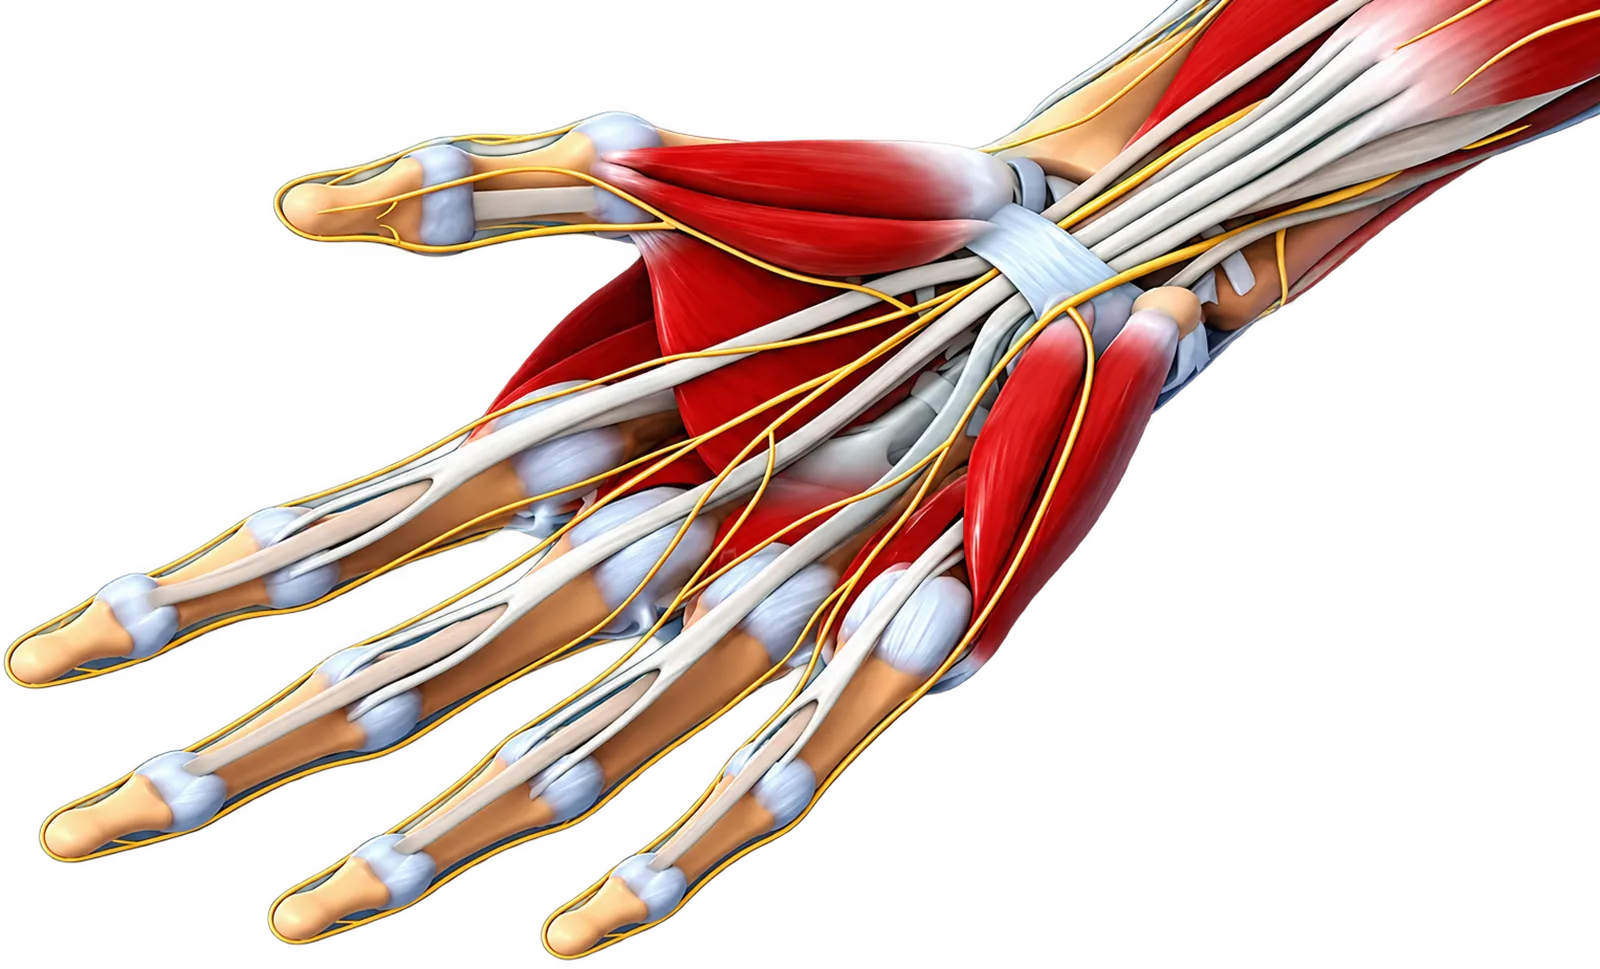
Transthyretin amyloidosis results from the deposition of misfolded proteins in tissues. At the wrist, these deposits accumulate in the synovium of the flexor tendons and in the transverse carpal ligament. They increase the volume of the structures contained within a non-expandable tunnel and compress the median nerve exactly as the idiopathic form does — but with an identifiable cause.
The mechanism is therefore the same: pressure rises in a canal that cannot expand. The difference lies in the origin: here, carpal tunnel syndrome is not an isolated mechanical accident, it is a warning sign of a diffuse disease.
What the figures say
Several studies converge to measure the frequency of this association.
These figures do not say that one carpal tunnel in five is amyloidosis. They say that, in a population of suggestive age and clinical presentation, the probability of finding amyloid deposits at the time of surgery is high enough to justify systematic biopsy.
The delay: five to ten years
Carpal tunnel syndrome usually precedes the clinical diagnosis of amyloid cardiomyopathy by five to ten years. This gap is what makes screening worthwhile: the hand surgeon sees the patient at the moment when treatment is most effective.
Figure 1 — The timeline of amyloidosis: the hand surgeon intervenes at the first stage, several years before cardiac involvement.
Among patients with a positive biopsy who underwent a cardiac work-up, 5 to 20% ultimately received a diagnosis of amyloid cardiomyopathy. A positive biopsy is therefore not a diagnosis of cardiac amyloidosis: it is a signal that justifies a work-up.
Who should be biopsied
The yield of screening depends entirely on selection. Not every carpal tunnel warrants a biopsy.
The most widely used criteria, drawn from the reference series, retain men aged 50 and over and women aged 60 and over undergoing carpal tunnel release. More recent series reach 29% Congo red positivity in 185 patients, with 80% wild-type transthyretin — a figure that mainly reflects an older selection.
A French series found bilateral carpal tunnel syndrome to be predictive in 38% of cases, with a mean age of 78 years among positive patients compared with 61 among negative ones.
The signals that favour biopsy:
- Man aged 50 and over, woman aged 60 and over
- Bilateral carpal tunnel syndrome, particularly when operated on in two stages — the most consistent sign
- Associated trigger finger
- Spontaneous rupture of the long head of biceps
- Lumbar spinal stenosis
- Atrial fibrillation or conduction disorder
- Unexplained left ventricular hypertrophy on echocardiography
Outside this profile, carpal tunnel syndrome remains idiopathic in the vast majority of cases, and biopsy adds nothing.
Which tissue to sample
Flexor tenosynovium is the reference specimen: it is used in roughly 62% of published studies. The transverse carpal ligament is an acceptable alternative — the two studies that compared them found a comparable prevalence of deposits.
Sampling both when exposure allows increases sensitivity at no added cost or morbidity.
There is no formal recommendation, but sampling generously avoids the classic problem: a fragment exhausted after staining and impossible to type afterwards. Studies that specify a threshold indicate a minimum of 0.3 cm² for the transverse carpal ligament and 0.5 cm² for tenosynovium. In practice, a square of about 1 cm guarantees enough material for Congo red staining and confirmatory mass spectrometry.
Technique, open and endoscopic
Open release. After division of the transverse carpal ligament, with the median nerve and tendons protected, a fragment of tenosynovium is excised. It takes a few seconds, with no added morbidity in any published series.
Endoscopic release. Sampling is feasible through the proximal portal: with the wrist in flexion to relax the tendons, an ulnar flexor tendon is hooked with a nerve hook, delivered through the incision, and the tenosynovium excised from its surface. A series of 282 cases directly compared the incidence of positive biopsies between the endoscopic and open approaches, with no loss of yield.
Biopsy therefore does not dictate the choice of approach: it is feasible with either technique. That said, if the tenosynovium is sparse or if exposure would require traction on the neurovascular bundle, I refrain rather than force the issue.
The pathology pathway
Immediate formalin fixation, paraffin embedding, Congo red staining, then examination under polarised light for apple-green birefringence. Some laboratories perform a preliminary thioflavin T screen, which is more sensitive under fluorescence, and confirm only positive specimens with Congo red.
The request must be explicit. Write "search for amyloid deposits — Congo red and polarised light". Tenosynovium sent without this note goes for routine staining, and deposits go unnoticed.
Ask for thick sections, 8 to 10 µm. Routine 3 to 4 µm sections underestimate birefringence.
Typing, the step too often skipped
A positive Congo red stain is not enough: the protein must be typed. Distinguishing wild-type transthyretin amyloidosis, hereditary transthyretin amyloidosis and AL amyloidosis changes prognosis and treatment entirely.
Yet this is the step most often omitted. In a survey of members of the American Society for Surgery of the Hand, 46% of surgeons who perform biopsies never send positive specimens for mass spectrometry.
The reference method is tandem mass spectrometry after laser microdissection, which can be performed on the paraffin block. Immunohistochemistry alone is unreliable for transthyretin amyloidosis. In France, the national amyloidosis network routes the block to a reference centre.
If transthyretin amyloidosis is confirmed, TTR gene sequencing distinguishes wild-type from hereditary disease. Where a pathogenic variant is found, genetic counselling and cascade family screening are offered.
What happens if the biopsy is positive
Cardiology referral is systematic, even in an asymptomatic patient. The work-up includes:
- ElectrocardiogramLooking for conduction disorders and for discordance between voltage and ventricular mass.
- Echocardiography with longitudinal strainLooking for apical sparing, highly suggestive of amyloid infiltration.
- Bone scintigraphy with HMDP or DPDWith Perugini grading: this is the investigation that allows non-invasive diagnosis of transthyretin amyloidosis.
- Serum and urine immunofixation, free light chainsAn essential step so as not to miss AL amyloidosis, the haematological emergency of the group.
In the EDUCATE study, two patients received a diagnosis of previously unsuspected AL amyloidosis, allowing treatment to begin without delay.
Since 2018, transthyretin stabilising therapies have transformed the prognosis of amyloid cardiomyopathy. This progress is what makes early diagnosis a real stake: intervening early, at the stage where carpal tunnel syndrome is still the only sign, means gaining years.
What this does not mean
Carpal tunnel syndrome is not a heart disease. The vast majority of cases remain idiopathic, and the message is not to cause alarm.
The aim is not to miss the diagnosis when the picture is suggestive — a man or woman in late middle age, bilateral involvement, associated signs. It is precisely in these cases that biopsy changes the patient's trajectory.